Part of the drug-class reference series. This page covers what depressants are, how the main ones work, and why some are far more dangerous than others.
Central nervous system depressants reduce arousal, slow mental processing, and lower neuronal excitability. The group includes alcohol, benzodiazepines, the older barbiturates, the “Z-drugs” used for sleep, GHB, kava, and — by effect if not by mechanism — the opioids.
They are among the most prescribed drugs in the world, and among the most misunderstood. Most of this page is about one molecule and one receptor, because most of the class converges on them.
The aim here is to explain why these drugs are prescribed, monitored and withdrawn the way they are — why one is started at a low dose and reviewed in a fortnight, why another is never stopped abruptly, why a prescriber asks what else you are taking before writing a script. The pharmacology is not an academic aside. It is the reasoning behind the caution.
A note on an old name
You will still encounter benzodiazepines called “minor tranquillisers” and antipsychotics called “major tranquillisers.” Both terms should be retired, and the reason is instructive.
The pairing implies a difference of degree — the same kind of drug at different strengths. In fact the two classes are unrelated. Antipsychotics act principally on dopamine pathways and are not CNS depressants in the pharmacological sense at all. A generation of prescribers inherited a naming scheme that made them look like neighbours.
The error has a specific origin. Chlorpromazine emerged from antihistamine research at Rhône-Poulenc rather than from psychiatry. The surgeon Henri Laborit was using it to induce what he called artificial hibernation in surgical patients before Delay and Deniker tried it in psychiatric patients in 1952. The sedation that earned it the tranquilliser label is largely antihistaminic and anti-adrenergic — essentially a side effect. The drug was named for the thing it incidentally did, not the thing it was for.
The practical point: sedation is a property, not a class. Several unrelated drug groups produce it by unrelated means, and grouping them by how they feel rather than how they work is how you end up with a dangerous mental model.
GABA: the brake
Gamma-aminobutyric acid (GABA, or 4-aminobutanoic acid, C₄H₉NO₂) is the principal inhibitory neurotransmitter in the mammalian brain. Its job is to make neurons less likely to fire.
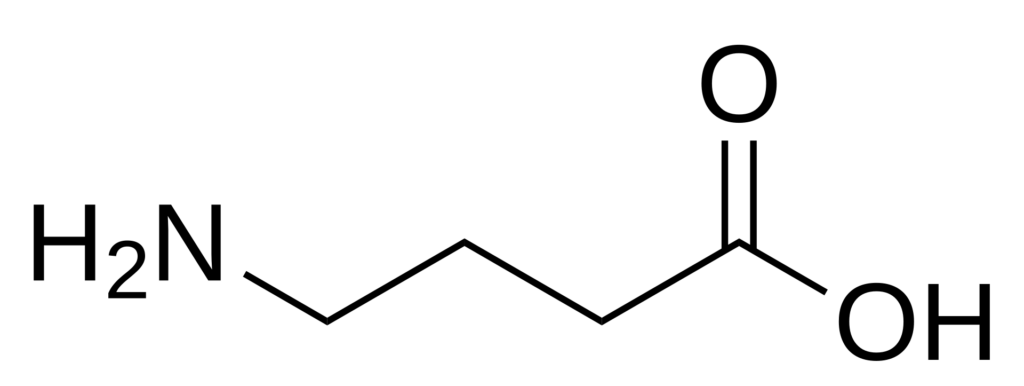
It is made from glutamate — the principal excitatory neurotransmitter — by the enzyme glutamic acid decarboxylase, using pyridoxal 5′-phosphate, the active form of vitamin B6, as a cofactor. The brain’s main brake is synthesised directly from its main accelerator, in a single enzymatic step.
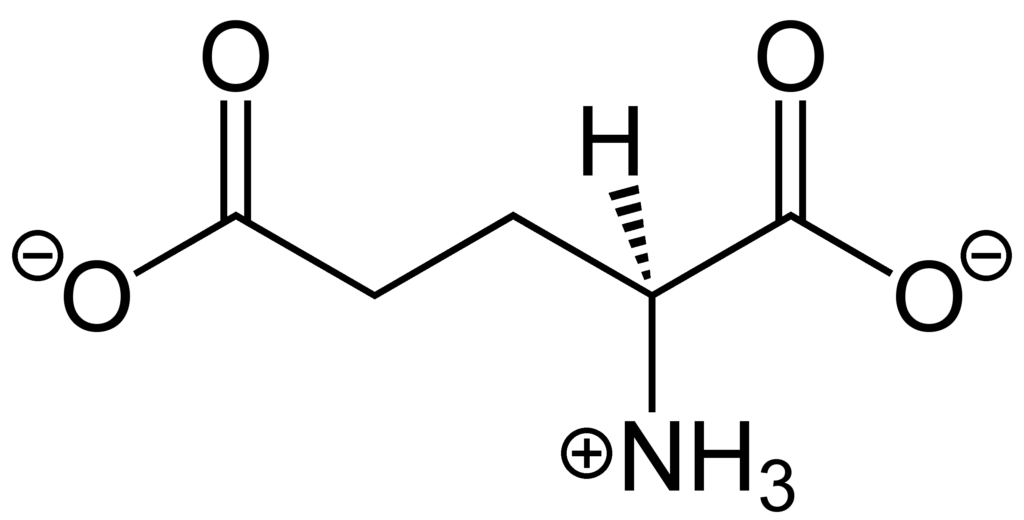
Two figures circulate for how much of the brain runs on glutamate, and they answer different questions. Across the brain as a whole, glutamate is the transmitter at more than half of all synapses. Within the cerebral cortex specifically, it accounts for up to 90% of synaptic connections — which follows from the cell populations, since excitatory pyramidal neurons outnumber inhibitory interneurons by roughly nine to one.
The 80–90% figure quoted in most textbooks is the cortical one. It is frequently repeated without that qualifier, which makes the brain sound more uniformly excitatory than it is.
What “inhibition” actually means
A neuron at rest holds a voltage difference across its membrane, with the inside negative relative to the outside — around −70 mV. When enough excitatory input arrives, that difference collapses and briefly reverses. This is depolarisation, and it is what propagates down the axon as an action potential.
Inhibition is anything that makes depolarisation less likely. GABA does this by hyperpolarising the cell — driving the interior still more negative, so a larger excitatory input is needed to reach threshold.
It is not that GABA switches neurons off. It raises the price of firing.
Two receptors, not one
This distinction explains several drugs that otherwise look like exceptions.
GABA-A is an ionotropic receptor — the receptor is the ion channel. It is a pentamer surrounding a central pore permeable to chloride. When GABA binds, the channel opens, chloride flows into the cell, and the interior becomes more negative. This is fast, millisecond-scale inhibition, and it is the target of benzodiazepines, barbiturates, Z-drugs, alcohol and kava.
GABA-B is metabotropic — a G-protein coupled receptor that works indirectly and more slowly, through potassium efflux and suppression of calcium influx. Baclofen is a GABA-B agonist; GHB acts here too. Benzodiazepines have no effect at GABA-B whatsoever.
When someone says “it works on GABA,” the useful follow-up is: which receptor?
Benzodiazepines and barbiturates: the critical difference
Both act at GABA-A. Both are positive allosteric modulators — they bind somewhere other than the GABA site and change how the receptor responds to GABA. Neither is a GABA substitute at ordinary doses.
The classic distinction is real and worth memorising:
- Benzodiazepines increase the frequency of channel opening. More openings, each of normal duration.
- Barbiturates increase the duration of channel opening. Fewer openings, each held open longer.
Either way, more chloride enters and inhibition increases.
Why this matters more than it looks
Here is the part that explains the entire safety difference between the two classes.
A benzodiazepine can only amplify GABA that is already present. No GABA, no effect. This gives the drug a ceiling: once every available receptor is being maximally modulated, additional drug achieves nothing further.
That ceiling is pharmacological, not clinical, and the distinction matters. Deep sedation from any cause carries its own dangers independent of the receptor — loss of airway protection and aspiration, hypoxic brain injury, rhabdomyolysis from prolonged immobility, and the complications of an extended intensive care admission. A ceiling on receptor modulation is not a ceiling on harm.
Barbiturates share that modulating action at low concentrations — but at higher concentrations they open the chloride channel directly, independent of GABA. The ceiling disappears. Inhibition continues deepening with dose, through sedation to anaesthesia to respiratory arrest, with no plateau in between.
This is why barbiturates have a narrow therapeutic index, and why phenobarbital now survives mainly in seizure control rather than as a sedative.
It is also why the first benzodiazepine was received as a major safety advance — though that arrival took longer than the usual shorthand suggests. Leo Sternbach synthesised chlordiazepoxide in 1955. Its therapeutic potential was not recognised at the time, and the compound sat without serious development for several years before testing revealed what it did. Hoffmann-La Roche marketed it as Librium in 1960.
Synthesis and arrival are five years apart, and the distinction is worth preserving: the molecule existed well before anyone understood it was useful.
Why a specific binding site makes a blocker possible
A drug that occupies a discrete, identifiable site on a receptor can in principle be displaced from it by a molecule that fits the same pocket without switching anything on. A drug that acts diffusely, or that gates a channel directly, offers nothing for a blocker to compete for.
This is why there is no antagonist for alcohol, and none for the barbiturates at the doses that matter. It is also why two such drugs do exist — and they are worth taking in the opposite order to the one you might expect.
Flumazenil mostly isn’t used. It occupies the benzodiazepine site and reverses sedation, and if you remember one thing about it, make it that reversal is usually the wrong move. Stripping the drug off the receptor in seconds produces abrupt withdrawal in anyone physically dependent, and seizures are the recognised consequence. The risk rises in mixed overdose — particularly where a proconvulsant such as a tricyclic antidepressant is also on board and the benzodiazepine has been incidentally holding seizures at bay. Its half-life is also short relative to many benzodiazepines, so a patient can resedate after appearing to recover.
It belongs to reversing procedural or iatrogenic oversedation in a monitored setting. It is not a general answer to benzodiazepine overdose, where supportive care and airway protection remain the mainstay. The existence of an antidote is not a reason to be relaxed about an overdose.
Naloxone: the one you can actually get
Opioids bind a specific receptor, so the same logic applies — and here the practical situation is entirely different.
Naloxone displaces opioids from the mu receptor and temporarily reverses an opioid overdose, restoring breathing. Unlike flumazenil, it is used routinely, and in Australia it is free, available without a prescription, and you can collect it for someone else.
The national Take Home Naloxone program supplies it at no cost through participating community pharmacies, needle and syringe programs and various services, with no prescription required. It comes as a nasal spray (Nyxoid) or a pre-filled injection (Prenoxad), both designed for use by people without medical training.
Eligibility is broader than most people assume. It covers anyone at risk of opioid exposure — including people taking prescribed opioids, not only illicit ones — and explicitly extends to family members, carers, friends, and anyone who might witness an overdose. It also now covers people using non-opioid illicit drugs, because potent synthetic opioids such as fentanyl have been found in supplies of methamphetamine, cocaine and ketamine.
If someone in your household takes opioids, having naloxone in the cupboard is reasonable and costs nothing. Call ahead, as not every pharmacy participates.
Naloxone buys time; it does not replace an ambulance. Call 000.
Why one drug is a sleeping tablet and another an anxiolytic
If benzodiazepines and Z-drugs act at the same receptor, why does zolpidem send people to sleep while diazepam calms them, relaxes muscle and stops seizures?
The answer is in the receptor’s construction. GABA-A is not one uniform protein but a pentamer assembled from a menu of subunits — typically two α, two β and one γ. The benzodiazepine binding site sits at the interface between an α and the γ subunit, so which α subunit is present changes how a drug behaves there. Subunit composition varies by brain region, which means the same drug does different things in different places depending on what is assembled locally.
The broad mapping, derived largely from mouse studies using point mutations that make individual subunits insensitive to benzodiazepines:
- α1 — sedation, amnesia, anticonvulsant effect
- α2 and α3 — anxiolysis and muscle relaxation
- α5 — learning and memory
Classic benzodiazepines such as diazepam bind all of these more or less indiscriminately, which is why they produce the full spread of effects — and the full spread of unwanted ones. Zolpidem preferentially binds α1-containing receptors, which is why it is marketed as a hypnotic rather than an anxiolytic, and why it is comparatively weak as a muscle relaxant.
This also explains a long-running disappointment. If anxiolysis sits at α2 and α3, a subunit-selective compound should in principle deliver calm without sedation — a benzodiazepine you could take before driving. Several were developed. None has become an established clinical option, and the gap between the elegant receptor story and the delivered drug is a useful reminder that mechanism does not guarantee medicine.
The subunit-to-effect mapping comes substantially from animal work and translates to humans imperfectly. Treat it as a good working model rather than settled fact.
The ones that don’t fit the GABA story
A common shortcut holds that depressants work by enhancing GABA. It is true of most of this page and false of several drugs routinely included in the class.
Opioids act at mu-opioid receptors — G-protein coupled, unrelated to GABA. They are CNS depressants by effect, not by mechanism. Their respiratory depression comes from direct suppression of brainstem respiratory centres.
Alcohol does enhance GABA-A, but that is a partial account. It is also an NMDA receptor antagonist — blocking glutamate, the accelerator, as well as boosting the brake — and acts at several other targets. The dual action is central to understanding withdrawal, where chronic suppression gives way to glutamatergic rebound.
GHB acts at GABA-B and at its own GHB receptors, not meaningfully at GABA-A.
Kava acts partly through GABA-A modulation, but kavalactones also affect sodium and calcium channels. Hepatotoxicity has been reported and is the reason for restrictions in several jurisdictions.
Why combinations are the real danger
Most fatal depressant overdoses involve more than one drug.
Two agents acting on the same receptor by different mechanisms can produce an effect substantially greater than either alone — a benzodiazepine increasing opening frequency while alcohol or a barbiturate acts elsewhere on the same channel. And because opioids suppress respiratory drive through an entirely separate pathway, combining an opioid with a GABAergic depressant converges on the same endpoint from two directions.
The benzodiazepine ceiling described above offers no protection here. It is a ceiling on that drug’s own action, not on the total depression achievable. This is the single most important practical fact on the page.
Dependence and withdrawal
The GABAergic depressants produce tolerance and physical dependence with sustained use, by mechanisms that include receptor downregulation. Liability varies considerably across the class, and the blanket claim that depressants are uniformly “highly addictive” is too coarse to be useful.
Withdrawal from GABAergic depressants — alcohol and benzodiazepines in particular — can be life-threatening, which distinguishes it from opioid withdrawal. Removing the brake from a system that has adapted by upregulating the accelerator produces unopposed excitation: tremor, autonomic instability, seizures, delirium. Neither alcohol nor long-term benzodiazepines should be stopped abruptly without medical supervision.
Quick reference
| Drug | Main target | Mechanism | Ceiling effect |
|---|---|---|---|
| Benzodiazepines | GABA-A | ↑ frequency of channel opening | Yes |
| Z-drugs | GABA-A (α1-selective) | ↑ frequency of channel opening | Yes |
| Barbiturates | GABA-A | ↑ duration; direct gating at high dose | No |
| Alcohol | GABA-A + NMDA | Enhances GABA, blocks glutamate | No |
| GHB | GABA-B, GHB receptors | Agonist | No |
| Kava | GABA-A, ion channels | Modulation | — |
| Opioids | Mu-opioid receptor | Not GABAergic | Partial, agonist-dependent |
This page is general information, not medical advice. If you take any of these medicines, do not change or stop them without speaking to your prescriber — withdrawal from some of them is genuinely dangerous.
If you are struggling, or thinking about harming yourself, please talk to someone.
- Lifeline — 13 11 14 (24 hours)
- Beyond Blue — 1300 22 4636 (24 hours)
- 13YARN — 13 92 76, for Aboriginal and Torres Strait Islander callers
- In an emergency, call 000
Your GP is also a reasonable first call, and a longer appointment can be booked for exactly this.

Leave a Reply